Central vision is lost or distorted while peripheral vision stays intact. This is the opposite of glaucoma.
Before you read
Test yourself first: 2 questions
Question 1 of 2
A nurse reviews the clinical picture of a client with amyotrophic lateral sclerosis (ALS). Which combination of findings is consistent with this disorder?
Answer: A. ALS is a progressive degeneration of both upper and lower motor neurons, producing muscle weakness, atrophy, fasciculations, and spasticity while sensation and cognition usually remain intact. Loss of sensation, relapsing-remitting vision changes, and a resting tremor are not characteristic of ALS.
Question 2 of 2
A nurse cares for a client with myasthenia gravis. Which statement best describes the underlying pathophysiology the nurse should understand?
Answer: B. Myasthenia gravis is an autoimmune disorder in which antibodies attack acetylcholine receptors at the neuromuscular junction, impairing nerve-to-muscle transmission and causing fluctuating, fatigable muscle weakness. It is not caused by dopamine deficiency, demyelination of central neurons, or motor neuron degeneration.
Keep the streak going with more questions like these, each with a full rationale.
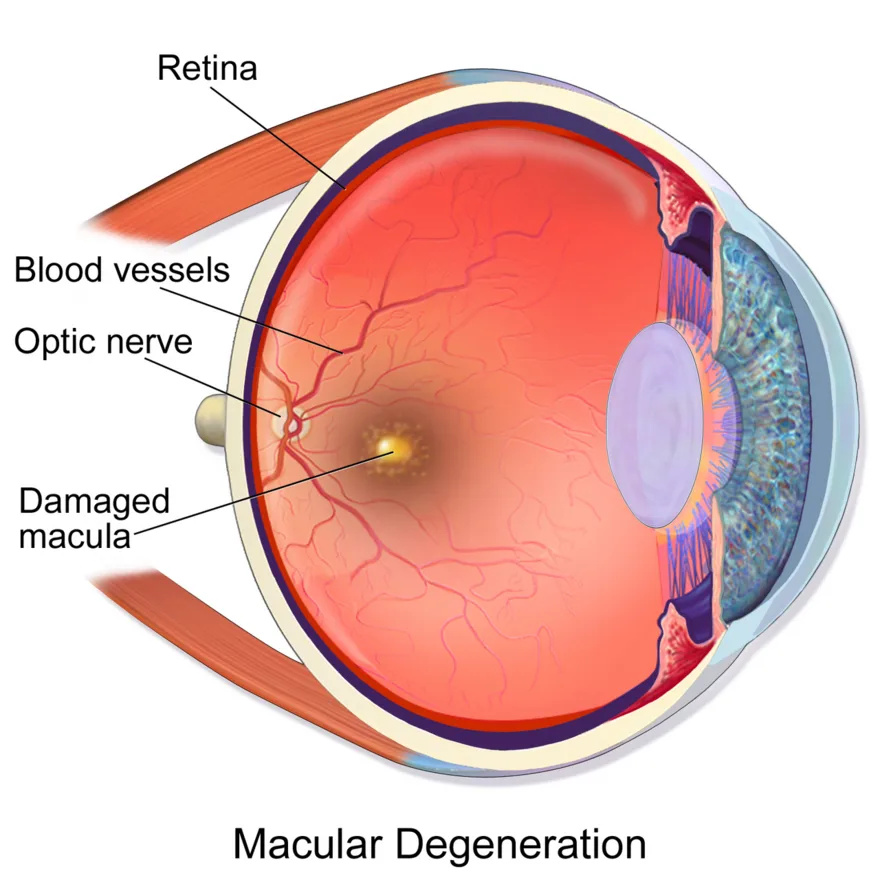
What is macular degeneration?
Among Americans over 60, it is one of the main reasons people lose their sight. In dry AMD, the macula's light-sensing cells wear away gradually. In wet AMD, abnormal blood vessels grow under the macula and leak blood and fluid, so damage happens quickly. Peripheral vision is spared. The nurse focuses on safety, early reporting of any change, and making the most of remaining vision.
Macular Degeneration illustrated
Key points to remember
- Central vision is lost or distorted while peripheral vision stays intact. This is the opposite of glaucoma.
- Dry (atrophic) AMD is the most common form. It progresses slowly with drusen deposits, and blurred central vision is its most common symptom.
- Wet (exudative, neovascular) AMD causes faster, more severe central loss. Its most common early sign is straight lines looking distorted or wavy (metamorphopsia), which is what the Amsler grid picks up.
- A central blind spot (scotoma) makes reading, recognizing faces, and fine detail work hard.
- Major risk factors: advancing age, smoking, family history, and Caucasian race.
- Treatment slows vision loss but cannot restore vision already lost. Wet AMD is treated with intravitreal anti-VEGF injections; AREDS antioxidant vitamins may be prescribed.
- The Amsler grid detects new distortion at home, and regular eye exams can find AMD before vision loss starts.
Signs & symptoms
- Central vision loss, blurry
- Straight lines look wavy
- Amsler grid for monitoring
Nursing priorities
- Assess how central vision loss affects daily safety (reading medication labels, stairs, cooking), because the environment must be adapted to remaining vision.
- Teach daily Amsler grid checks, one eye at a time, with immediate reporting of new distortion, because sudden change may mean conversion to wet AMD and treatment is time-sensitive.
- For wet AMD, prepare and support the patient through intravitreal anti-VEGF injections, because they slow abnormal vessel growth.
- Arrange low-vision aids (magnifiers, large print, high-contrast lighting) and vision rehabilitation, because they help the patient use remaining peripheral vision.
- Encourage smoking cessation, dark leafy greens, and prescribed AREDS vitamins, because smoking is a major risk factor the patient can change.
Worked example
- Cue: An older adult with dry AMD says door frames suddenly look bent in the right eye and reading has become blurrier over a few days.
- Meaning: New distortion with rapid change suggests possible conversion to wet AMD.
- Action: Notify the provider and arrange urgent ophthalmology evaluation; review home safety in the meantime.
- Evaluation: Wet AMD is confirmed, anti-VEGF injections begin, and the patient correctly demonstrates one-eye-at-a-time Amsler grid checks.
Patient teaching
- Look at the Amsler grid every day, covering one eye at a time. Call right away if lines look wavy or part of the grid is missing.
- Stop smoking, eat dark leafy green vegetables, and take the eye vitamins your provider prescribed.
- Bright lighting, magnifiers, large print, and high contrast make tasks easier. Your side vision stays, and you can learn to use it.
- Keep regular eye exams. Treatment works best when changes are caught early.
Common mistakes
- Mixing up AMD and glaucoma: AMD takes central vision and spares peripheral vision; glaucoma is the opposite pattern.
- Telling a patient that injections or vitamins will bring vision back. Treatment only slows loss.
- Calling flashes, floaters, or a curtain over vision 'AMD progression.' That pattern suggests retinal detachment.
- Teaching Amsler grid checks with both eyes open instead of one eye at a time.
Red flags: report now
- Sudden worse central vision, new wavy lines, or a new blank spot — arrange urgent ophthalmology evaluation for possible wet AMD.
- New flashes, floaters, or a curtain over vision — suspect retinal detachment, a separate emergency; escalate now.
- Patient wants to stop injections for an unproven 'cure' — reinforce that lost vision does not return and treatment slows further loss; inform the provider.
References
Clinical references for this topic